Drug Channels delivers timely analysis and provocative opinions on pharmaceutical economics and the drug distribution system. Drug Channels reaches an engaged, loyal and growing audience of more than 100,000 subscribers and followers. Learn more...
It’s time for Drug Channels’ annual look at pharmacist salaries and employment. The latest data might be a tough pill to swallow.
As we predicted, the situation was grim for retail pharmacists. Employment in retail outpatient pharmacies fell by 8,200 positions in 2025, following a drop of 11,700 positions over 2023 and 2024 combined.
Meanwhile, pharmacist employment at hospitals grew by 3,000 positions, after hospitals added more than 11,000 pharmacist jobs in 2023 and 2024. Nearly half of all pharmacists now work outside a traditional retail setting.
Overall pharmacist salaries averaged $140,920, but varied widely across practice settings. Salary growth in many settings, however, did not keep pace with overall inflation.
Our 2026 Economic Report on U.S. Pharmacies and Pharmacy Benefit Managers documents how and why retail pharmacy economics are under sustained pressure. Since 2018, the two remaining national drugstore chains have collectively closed nearly 3,000 locations, reflecting margin compression and weaker front-end economics.
Informa’s PBM Contracting Summit
December 8-9, 2026 | Chicago, IL Drug Channels readers save 10% with code 26DRCH10*
The PBM Contracting Summit returns to Chicago this December! Join the industry as expert speakers navigate the complex PBM landscape, gaining unparalleled strategies to enhance patient care and effectively manage costs.
Key topics covered:
Employer and Broker Priorities: Understand what drives PBM selection, where traditional models fall short, and how to demonstrate measurable value.
Federal Regulatory Reform: Explore how evolving policy and enforcement affect your contracts through interactive roundtables.
GLP-1 Cost Management: Balance growing demand with access, affordability, and long-term sustainability.
Alternative PBM Models: Examine how emerging models address employer demands for transparency and control.
Manufacturer Direct-to-Consumer Strategies: Assess how direct channels and patient support programs are reshaping the PBM’s role.
The PBM Contracting Summit remains essential to tackle rising drug costs head-on, spotlighting bold innovations in contracting, GLP-1 strategy, AI-powered solutions, and federal and state-driven regulatory change.
View the agenda for PBM Contracting 2026 to see the complete picture—the program, speakers, and more. Visit www.informaconnect.com/pbm-contracting for further details and to register.
Drug Channels readers will save 10% off when they use code 26DRCH10 and register prior to November 6, 2026.*
*Cannot be combined with other offers or used towards a current registration. Cannot be combined with special category rates or other offers. Other restrictions may apply.
The content of Sponsored Posts does not necessarily reflect the views of HMP Omnimedia, LLC, Drug Channels Institute, its parent company, or any of its employees. To find out how you can publish an event post on Drug Channels, please contact Marie Caldwell(mcaldwell@hmpglobal.com)
Today's guest post comes from Kristen Magee, Vice President of Methodology & Enablement at AssistRx.
Kristen explains why patient support programs (PSPs) need to evolve as products move from launch through growth, maturity, and loss of exclusivity. She outlines how manufacturers can recalibrate the balance of technology, automation, and human support at each stage to improve efficiency while maintaining strong patient and healthcare provider experiences.
Football season is officially back. Personally, my signal is hearing my uncle curse about bad calls from 1,000 miles away, but you may have already seen a game.
This news roundup is short enough to fit into an ad break or two. *Caveat: may lead to rabbit holes that take much longer than an ad break.
Drug Channels Institute is proud to host the 2027 Drug Channels Leadership Forum, which will take place from March 15–17, 2027, in Miami. Request your invitation to this invite-only gathering of senior leaders from across the drug channel ecosystem. You must request an invitation to be considered for attendance. We will begin sending invitations in mid-October.
Today's guest post comes from Divya Iyer, SVP, Head of Revenue, Pharma Direct at GoodRx.
Divya examines how AI-powered search and conversational tools are reshaping the way patients research treatments and prescription costs before ever reaching a brand's website. She argues that pharmaceutical manufacturers must rethink their direct-to-consumer (DTC) strategies to ensure treatment information is discoverable, trusted, and connected to actionable next steps.
For more than a decade, the answer to “Where do drug wholesalers make their money?” has been generic drugs.
Although wholesaler revenues are linked most closely to sales of brand-name drugs, the majority of wholesalers’ gross profits comes from generic drugs. We estimate that in calendar year 2026, generic drugs will contribute 52% of total drug distribution gross profits of the Big Three wholesalers, but only 9% of drug distribution revenues.
Generic drugs are the long-running hit show that has carried wholesalers' profits for 15+ seasons. The show is still on the air, but a supporting character is starting a spinoff.
Generic drugs’ share of distribution gross profits has declined, from 68% in 2022 to 52% in 2026. This partially reflects the growth in profits from provider-administered biosimilars. Biosimilars now account for 6% of wholesalers’ drug distribution revenues, but 23% of total gross profits.
November 17-20, 2026 | Sheraton Downtown Philadelphia Exclusive Offer – Use promo code 26DC10 to save 10% on your registration*
Patient need is at an all-time high and the healthcare ecosystem is more complex than ever. With insurance changes, policy volatility, AI disruption and economic pressures reshaping patient programs, staying ahead is critical.
Join industry leaders at Patient Pathways 2026, where experts in copay, reimbursement and patient services will share actionable insights, innovative solutions and best practices. Unlock cutting-edge copay and reimbursement strategies, innovative patient solutions and robust compliance frameworks to elevate program performance, remove barriers and maximize affordability impact.
Can’t-Miss Highlights:
27+ hours of cutting-edge content featuring 6+ sessions on AI integration and automation, 10+ sessions on navigating regulatory changes and compliance frameworks, 20+ sessions on operational challenges and more.
Expert speakers from leading organizations such as Pfizer, BMS, Sanofi, Vertex, Boehringer Ingelheim, Teva, Novo Nordisk and more.
In-depth case studies on topics including patient cost-sharing burdens, balancing affordability with care and market saturation impacts.
Regulatory and policy updates to stay compliant and proactive in a rapidly evolving healthcare landscape.
15+ hours of networking opportunities to connect with industry leaders, build strategic partnerships and expand your professional network.
Why Attend?
Balancing patient services with business objectives is a delicate task. The Congress will address critical questions that access professionals face:
How can programs remain sustainable, innovative and profitable while supporting patients?
How will upcoming health policy changes impact affordability, commercialization and program strategies?
Is your program equipped to deploy AI strategically?
Join industry leaders, peers and solution providers for answers to these questions and more – Benchmark best practices, gain actionable insights, connect with industry trailblazers and drive patient support and affordability forward at Patient Pathways 2026.
“The event was exceptionally well-organized, the atmosphere was welcoming, and I left feeling more informed, empowered and excited to bring what I learned back to my team.”
*Cannot be combined with other offers, promotions, or applied to an existing registration. Other restrictions may apply.
The content of Sponsored Posts does not necessarily reflect the views of HMP Omnimedia, LLC, Drug Channels Institute, its parent company, or any of its employees. To find out how you can publish an event post on Drug Channels, please contact Marie Caldwell(mcaldwell@hmpglobal.com).
Today's guest post comes from Tom Traylor, Senior Vice President of Pharmacy Operations at CareMetx.
Tom examines how intake speed and time to therapy relate to each other in specialty pharmacy programs. He describes how bringing pharmacy connectivity to the front of the patient journey can support faster benefit verification, clearer affordability answers, and shorter time to therapy.
The U.S. prescription drug market continues to expand, but the foundations of the drug channel are shifting. Legislative intervention, pricing realignment, vertical integration, and alternative payment models are accelerating a transition away from a rebate-driven system built on high list prices and toward a marketplace increasingly shaped by net prices.
DCI’s seventeenth annual report examines what these changes mean for the pharmaceutical wholesalers and specialty distributors at the center of the U.S. drug channel. With nine chapters, more than 400 pages, 193 exhibits, and more than 930 endnotes, this report is unmatched in scope and depth.
Preorder today to secure the fully updated, revised, and expanded 2026-27 edition at special discounted prices. Preorders also ensure early access. You will receive the report before its October 12 release date.
Special preorder and launch pricing discounts will be available through October 26, 2026. Act now to maximize your savings.
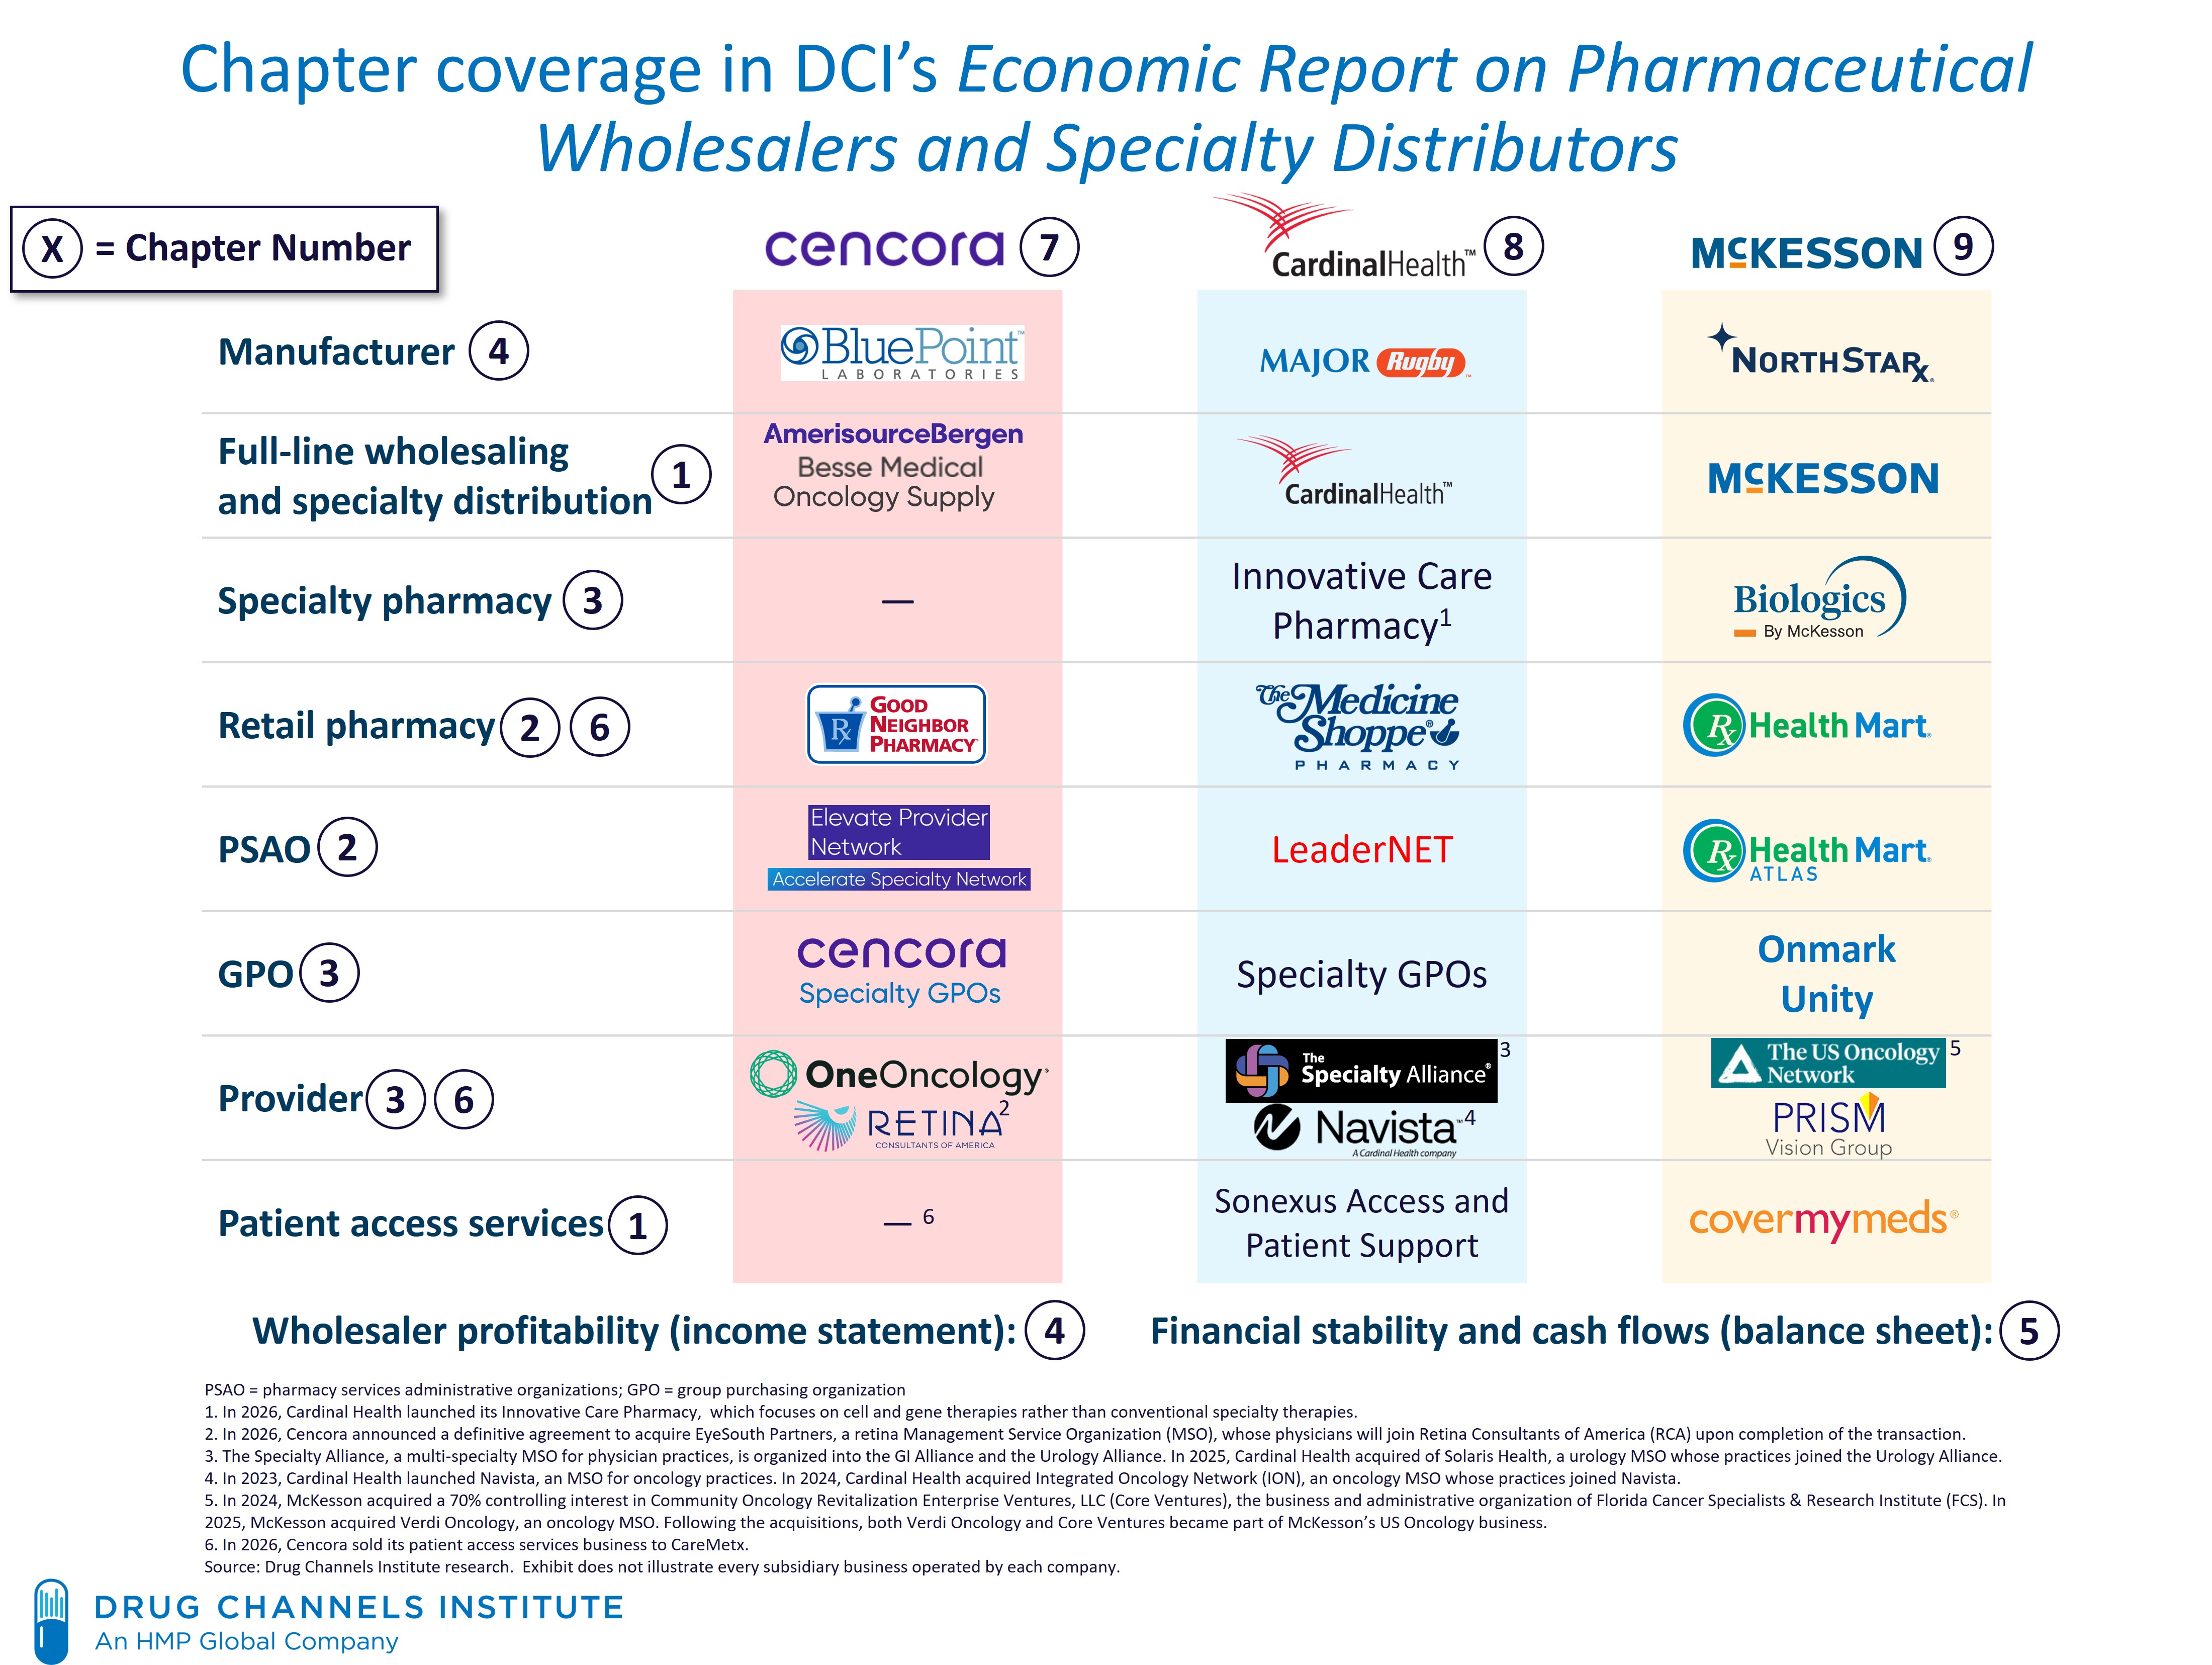
The chart below highlights the vertical alignment and diverse roles of Cencora, Cardinal Health, and McKesson within the U.S. healthcare system. The circled numbers identify the report chapters that explain and analyze each business.
[Click to enlarge]
The new edition provides the most current financial and industry data about pharmaceutical distribution. Among the major findings and expanded areas of coverage:
Drug distribution revenues for the Big Three public wholesalers are projected to reach $933 billion in 2026, although growth has slowed from double-digit to mid-single-digit rates.
The largest wholesalers have invested more than $20 billion in physician management services organizations, transforming their roles in buy-and-bill markets.
Changes in drug pricing, direct-to-patient models, and other emerging channels are accelerating the industry’s transition toward a Net Pricing Drug Channel.
The report examines the evolving economics of biosimilars, cell and gene therapies, the 340B Drug Pricing Program, and implementation of the Inflation Reduction Act.
DCI’s proprietary economic models reveal differences in the business strategies, market positions, financial performance, and underlying profitability of Cencora, Cardinal Health, and McKesson.
There are 193 exhibits in the 2026-27 edition, compared with 187 in last year’s report. Most are new or fully updated.
Thank you for your continued interest in our research. Please email us (dcisupport@hmpglobal.com) with any questions before purchasing. We look forward to sharing this year’s insights with you.
Informa’s Pharma/Biotech GTN Summit returns on November 16-18, 2026, in Philadelphia, PA, bringing together hundreds of senior finance, gross-to-net and accounting professionals from across the life sciences industry to navigate the evolving complexities of gross-to-net management in an era of unprecedented regulatory change.
This year’s CPE-accredited event (offering up to 16.0 CPE credits, plus 2.0 additional credits with the optional add-on, pre-conference training course) will deliver cutting-edge insights on AI integration, IRA implementation strategies, and advanced forecasting methodologies. With an intensive focus on regulatory adaptation, technology transformation, and cross-functional excellence, the agenda addresses the most pressing challenges facing GTN professionals today – from Maximum Fair Price (MFP) operationalization to AI-powered analytics and strategic organizational design.
Featured Thought Leaders Include:
Brett Nussbaum, Head of Gross to Net Accounting, Novartis
Matt Pellegrini, Senior Director Business Finance, NA, Teva Pharmaceuticals
*Offer exclusively for life sciences manufacturers only. Offer applies to the current rate and maybe not be applied to existing registrations; additional terms may apply, see website for full details.
The content of Sponsored Posts does not necessarily reflect the views of HMP Omnimedia, LLC, Drug Channels Institute, its parent company, or any of its employees. To find out how you can publish an event post on Drug Channels, please contact Marie Caldwell(mcaldwell@hmpglobal.com).
We’re excited to announce the return of the Drug Channels Leadership Forum (DCLF), taking place March 15–17, 2027, at the JW Marriott Miami Turnberry Resort & Spa in Miami. Drug Channels Institute (DCI) will once again host this invitation-only gathering of senior leaders and decision-makers from across the drug channel.
DCLF returns for its third year with the same focus that has defined the event from the start: candid, consequential conversations about the forces reshaping the U.S. pharmaceutical ecosystem.
Today's guest post comes from Geoffrey Chaiken and Matthew Chaiken, Co-founders of BlinkRx.
Geoffrey and Matthew examine how efforts to improve patient access have contributed to an increasingly fragmented prescription journey. They suggest that a more integrated approach can reduce complexity, improve visibility and control for manufacturers, and create a simpler path to therapy for patients.
PBM-affiliated private label biosimilars would seem to have a built-in formulary advantage. But for ustekinumab, that advantage has not carried over to Medicare Part D.
A recent JAMA Network Open study identified 12 ustekinumab products available for formulary coverage in early 2026. Yet the average Part D plan covered only 2.3 biosimilars. Even more surprising, PBM affiliated private label products were largely missing from formularies connected to their corporate siblings.
CVS Health’s Cordavis labeled Pyzchiva received no Part D coverage. Optum Rx’s Nuvaila labeled Wezlana appeared in just 0.4% of UnitedHealth plans.
The results run against the conventional logic of vertical integration. If a PBM can influence formulary placement, why not direct volume toward its own product like in commercial formularies? The answer lies in the Inflation Reduction Act’s (IRA) Part D redesign, which made the economics of an affiliated private label biosimilar potentially less attractive in Medicare than in the commercial market.
Below, we follow the incentives that help explain why PBM-affiliated biosimilars remain largely absent from Medicare Part D formularies.
Today's guest post comes from Bryce Aronson, Director of Business Development at AssistRx.
Bryce covers three considerations taking effect in January 2027—the end of Medicare Part D premium support, a faster Medicaid redetermination timeline, and the shift away from once-a-year reverification—and what they mean for patient support programs. He explores how affordability solutions can help reduce coverage disruptions, minimize unnecessary PAP utilization, and maintain continuity of therapy throughout the transition.
Today's guest post comes from Jay Weaver, VP, Payer Solutions at PANTHERx® Rare.
Jay describes the clinical and operational work that often happens behind the scenes at a Rare Pharmacy. He explains how these capabilities—including greater personalization, real-world evidence, and specialized clinical expertise—can support therapeutic success and help payers assess the value of Rare Pharmacy.
The FDA’s removal of CAR-T REMS requirements eliminates one obstacle to expanding treatment beyond traditional academic medical centers. That change could disproportionately benefit the Big Three wholesalers, which have spent billions building positions in community oncology while simultaneously investing in cell-and-gene-therapy distribution and support infrastructure.
Read on for our review of this dynamic sector and ponder how wholesalers’ community oncology roll-up activities could interact with their cell and gene therapy (CGT) investments. Will wholesalers capture a growing share of CAR-T’s economics, or will hospitals continue to hold the upper hand?
Today's guest post comes from Josh Marsh, Vice President and General Manager at Cardinal Health Sonexus™ Access and Patient Support.
Josh examines the risks manufacturers take when transitioning a patient services hub from one vendor to another. He argues that scaling with a proven, flexible blueprint can help hubs with speed, patient continuity, and confident decision-making.
The United States has almost 8,000 fewer retail pharmacies than it did in 2018, and more than 2,000 closed in 2025 alone. Rite Aid has liquidated. Walgreens is working through a multi-year plan to shutter hundreds of stores. CVS has trimmed hundreds more.
Yet total U.S. prescription dispensing revenues for all dispensing formats reached a record $751 billion in 2025, up 10% from 2024.
Record closures and record revenue in the same year may seem contradictory, but national totals obscure very different effects on the community. The impact of the retail pharmacy shakeout on patient access has become geographically K-shaped: dense markets can absorb pharmacy closures with little loss of patient access, while rural communities can lose their only nearby pharmacy.
The economic pressures on pharmacies are similar across the country. The access consequences of a closure are not. Below, we examine what is driving the shakeout and why geography determines which communities can absorb them.
Informa Connect’s Medicaid Drug Rebate Program Summit October 5-7, 2026 | Chicago, IL
Drug Channels readers save 10% with code 26DRCH10* View Agenda | Download Brochure
The Medicaid Drug Rebate Program Summit returns to Chicago this October! Join 700 annual attendees and nearly 90 expert speakers to master complex regulatory guidelines to deliver compliant government pricing and reporting programs.
The 2026 event features:
Direct state engagement: One-on-one Medicaid dispute resolution with 31+ confirmed states.
Comprehensive coverage: MFP implementation, inflation rebates first invoicing, pharma tariffs, Buy America rules, onshoring strategies, PBM reforms, FTC transparency mandates, and physician-administered product challenges, 340B, AMP, URA, GTN, SPTR, FMV, FSS, Medicaid Parts D and B, and more.
Unparalleled faculty: Industry leaders from Gilead, AbbVie, Amgen, AstraZeneca, Genentech, Eli Lilly; legal authorities from Hogan Lovells, Arnold & Porter, Covington & Burling; government representatives including CMS, OIG, VA, and 31+ state Medicaid agencies.
Networking: Opportunities to build valuable connections with more than 700 annual attendees.
Prior attendees praise the event as “An excellent forum to meet industry professionals and gain insight into best practices, current and future, of what’s to come regarding manufacturers and government regulations.”
The MDRP Summit remains essential for anyone navigating the complex intersection of pharmaceutical economics, compliance, and government programs. With expert speakers, targeted sessions, and valuable networking opportunities, this event delivers actionable insights you can implement immediately.
View the agenda for MDRP 2026 to see the complete picture – the program, speakers, and more, and visit www.informaconnect.com/MDRPSummit for further details and to register.
Drug Channels readers will save 10% off when they use code 26DRCH10 and register prior to September 18, 2026.*
*Cannot be combined with other offers or used towards a current registration. Cannot be combined with special category rates or other offers. Other restrictions may apply.
The content of Sponsored Posts does not necessarily reflect the views of HMP Omnimedia, LLC, Drug Channels Institute, its parent company, or any of its employees. To find out how you can publish an event post on Drug Channels, please contact Marie Caldwell(mcaldwell@hmpglobal.com).
Today's guest post comes from Scott Filosi, Chief Commercial Officer at Valeris.
Scott explores how patient access organizations can move beyond simply tracking the patient journey to using real-time insights to improve it. He argues that connecting commercial strategy, market access, payer intelligence, and patient services can speed access to therapy, improve decision-making, and enhance the patient experience.
In late June, the boffins at the Centers for Medicare & Medicaid Services (CMS) released the latest projections for U.S. spending on healthcare. (See links below.) These data provide the latest official, nonpartisan look at the future of U.S. healthcare spending.
Notably, overall U.S. spending on drugs dispensed by retail and mail pharmacies will remain about 9% of overall healthcare spending.
Below, we outline the factors that led to the dramatic revision to Medicare spending, along with insights on the shrinking role of private insurance and consumer out-of-pocket spending.
Taxpayers—primarily via Medicare and Medicaid—now account for a majority of U.S. prescription drug spending, outstripping the share financed via employer-sponsored insurance.
Today's guest post comes from Jen Norton, President, Market Access & Value at EVERSANA.
Jen examines why fragmented ownership across development, regulatory, pricing, distribution, and field functions undermines access at launch. She argues that naming a single accountable owner for the access outcome can close "access debt" earlier, reduce pre-launch friction, and turn coverage into real patient access.
Today's guest post comes from Chip Parkinson, CEO at Gifthealth.
Chip discusses how Direct-to-Patient (DTP) models can transform the manufacturer access model for prescription therapies. He argues that a tech-plus-touch, end-to-end approach can improve patient access, protect manufacturer economics, and increase brand trust and loyalty.
Every year, Drug Channels reviews drug pricing trends at the largest pharmaceutical manufacturers. This year's disclosures provide early evidence that the economics of the U.S. drug channel—and the strategies manufacturers use to secure market access—are beginning to change.
We review the following eight companies: Bristol Myers Squibb, Eli Lilly and Company, Genentech, GlaxoSmithKline, Sanofi, Takeda, Teva, and UCB. You can find links to each company’s data in the appendix.
Our review found:
Brand-name drug list prices continued to rise modestly, while mandatory and voluntary rebates, discounts, and fees reduced net prices at seven of the eight manufacturers.
The average gross-to-net price difference was –5.5%, reflecting an average list price increase of 3.7% and an average net price decline of 1.8%.
For the three manufacturers that disclosed these data, rebates, discounts, and other fees reduced the selling prices of brand-name drugs to less than half of their list prices.
Sanofi's latest and historical disclosures provide one of the clearest illustrations yet of the drug channel's changing economics. Since 2020, the company's estimated U.S. biopharmaceutical sales have grown far faster than rebate payments. As a result, the share of its gross sales returned to payers as rebates declined from 51% to 39%.
Taken together, this year's manufacturer disclosures suggest that the gross-to-net bubble is growing more slowly—and even deflating in parts of the market. Meanwhile, the Net Pricing Drug Channel (NPDC) is becoming visible in manufacturers’ pricing disclosures and financial statements.
Today's guest post comes from Divya Iyer, SVP, Head of Revenue, Pharma Direct at GoodRx.
Divya examines why direct-to-consumer strategies shouldn't default to mail-order as the endpoint for every program. She argues that preserving patient choice between retail pickup and home delivery can reduce friction, improve therapy initiation, and strengthen the overall patient experience.
The 340B Drug Pricing Program continues to redefine the meaning of "skyrocketing."
For 2025, discounted purchases under the 340B program reached an astounding $100 billion—23% higher than in 2024.
The gross-to-net difference between list prices and discounted 340B purchases—a proxy for funds available to covered entities—also grew, to $79.5 billion (+$12.0 billion).
Hospitals again accounted for 87% of 340B purchases.
340B purchases are now more than 70% larger than Medicaid’s net prescription drug spending. The program now accounts for nearly one-fifth of the total U.S. gross-to-net bubble.
During DCI’s June webinar, I predicted that the 340B program would move from an era of expansion and opacity to one of transparency and accountability.
But given the latest growth figures, I worry that reform of this undermanaged, out-of-control program may never happen. Has the program become too big to reform?
Read on for our full analysis—and consider whether 340B will ever face its true day of reckoning.
Provider-administered drugs are one of the fastest-growing and least-managed cost drivers for commercial plan sponsors.
Despite that, recent data from the Pharmaceutical Strategies Group show that only 35% of commercial plan sponsors currently have a site of care (SOC) program in place for specialty pharmacy. That result is surprising given the size of the savings at stake.
Medicare has figured this out and started site-neutral payments over a decade ago, but the employers who fund the bulk of commercial health spending largely haven't.
The evidence supporting SOC management is no longer the story. The real question is why so many commercial plans continue paying hospital prices when lower-cost alternatives already exist.
Today's guest post comes from Megan Wetzel, Vice President of Product, Access and Affordability at CoverMyMeds.
Megan examines how prior authorization execution has become a strategic differentiator for biopharma brands as formulary changes and expanding utilization management put more pressure on access. She argues that building consistent, scalable prior auth execution can reduce therapy delays, improve determination time, and strengthen brand performance across the product lifecycle.
Whether you support or oppose the current structure of 340B, it is becoming harder to ignore that the debate is expanding beyond manufacturers and hospitals. Employers, health plans, and policymakers are beginning to ask who ultimately finances the program—and what those economics mean for benefit costs and premiums.
Today’s guest post comes from Geoffrey Chaiken and Matthew Chaiken, Co-founders of BlinkRx.
Geoffrey and Matthew examine the important role of patient services providers. They suggest several questions manufacturers can ask when evaluating a patient services partner’s technology infrastructure, pharmacy network design, data visibility, and operational capabilities.
It’s time for Drug Channels’ annual look at pharmacist salaries and employment. The latest data might be a tough pill to swallow.
As we predicted, the situation was grim for retail pharmacists. Employment in retail outpatient pharmacies fell by 8,200 positions in 2025, following a drop of 11,700 positions over 2023 and 2024 combined.
Meanwhile, pharmacist employment at hospitals grew by 3,000 positions, after hospitals added more than 11,000 pharmacist jobs in 2023 and 2024. Nearly half of all pharmacists now work outside a traditional retail setting.
Overall pharmacist salaries averaged $140,920, but varied widely across practice settings. Salary growth in many settings, however, did not keep pace with overall inflation.
Our 2026 Economic Report on U.S. Pharmacies and Pharmacy Benefit Managers documents how and why retail pharmacy economics are under sustained pressure. Since 2018, the two remaining national drugstore chains have collectively closed nearly 3,000 locations, reflecting margin compression and weaker front-end economics.
Today’s guest post comes from Nareda Mills, President of Patient Solutions at Inizio Engage.
Nareda examines how growing access complexity is reshaping specialty commercialization. She explores the emerging role of Non-Dispensing Pharmacies (NDPs) and argues that by improving coordination, visibility, and patient engagement, they can accelerate time-to-therapy and create a more seamless access experience.
For years, Medicare Part D plans often preferred high-list/high-rebate branded multiple sclerosis (MS) drugs over lower-cost generics. That was rational behavior inside an irrational system.
The Inflation Reduction Act (IRA) offers one example of how incentives can change behavior in the system. New research in JAMA Health Forum reveals a significant reversal in Medicare Part D formulary coverage for MS drugs. After years of plans favoring brand-name drugs over generics, 2025 formularies shifted to near-universal generic coverage.
However, in return patients got narrower formularies, higher upfront costs, and way more taxpayer dollars spent than expected.
While this wasn’t the case for all drug classes, in MS, the IRA Part D redesign has forced plans to care more about net drug spending. Below, we analyze the formulary data and explain why the coverage patterns changed so abruptly—and what new tradeoffs have emerged.
Minnesota’s new 340B data reveal a growing disconnect between the program’s size and the value Minnesotans receive in return.
In 2024, nonprofit hospitals generated more than $1.3 billion in 340B net profits—nearly a billion dollars more than they provided in uncompensated care. At the same time, these same institutions already benefit from substantial tax exemptions tied to their not-for-profit status and charitable mission.
The gap between 340B profits and charity care isn’t a rounding error or a one-off anomaly. The 340B Drug Pricing Program has evolved into a significant profit center for hospital systems. This is another layer on top of existing public subsidies, not a substitute for them.
As you’ll see below, our analysis describes a 340B program that generates financial gains far in excess of any contribution back to the people of the state. There is also no clear accountability for how those dollars are used.
Drug Channels Institute’s (DCI’s) latest analysis reveals that PBM-affiliated specialty pharmacies continue to dominate the dispensing of specialty drugs.
For 2025, DCI has identified more than 1,900 dispensing locations with specialty pharmacy accreditation from one or both of the two major independent accreditation organizations. The overall number of accredited locations grew by only 3% in 2025, but is more than five times larger than the 2015 figure.
However, market share for the dispensing of specialty drugs remains highly concentrated. For 2025, the three largest specialty pharmacies accounted for two-thirds of total prescription revenues from pharmacy-dispensed specialty drugs. These businesses are all owned by vertically integrated organizations that also own a PBM.
Below, we share DCI’s latest analysis of the top 15 specialty pharmacies, including updated market shares and revenue estimates, highlighting how vertical integration and channel control continue to reshape specialty dispensing. Despite growth in accredited locations, economic power remains concentrated among a small group of PBM-affiliated entities.
It's time for Drug Channels Institute’s (DCI) annual update of vertical integration among insurers, PBMs, specialty pharmacies, and healthcare services within U.S. drug channels. As you can see below, we have updated and revised our infamous illustration of the major vertical business relationships within the largest companies.
These organizations continue to exert greater control over patient access, sites of care/dispensing, and pricing, although some have started to unwind their vertical integration strategies. Scrutiny of these companies’ actions continues to grow.
Three is still the magic number for pharmacy benefit managers (PBMs).
For 2025, 80% of all equivalent prescription claims were processed by three companies: the CVS Caremark business of CVS Health, the Express Scripts business of Cigna, and the Optum Rx business of UnitedHealth Group. Express Scripts continued to pull ahead of its peers, while CVS Caremark’s claim volume declined for the second year.
Independent PBMs continued to gain business from these larger PBMs, showing fragmentation at the margins. Many smaller PBMs still rely on their larger competitors for claims processing, network management, and rebate negotiation. So even if a plan sponsor chooses an alternative PBM, the Big Three can still win with behind-the scenes economics.
The Big Three PBMs’ dominance persists, but they face growing regulatory and competitive constraints. The largest PBMs are restructuring their businesses in response to client demands, legislative changes, and legal pressures. The emerging Net Pricing Drug Channel will accelerate these shifts, forcing changes in how PBMs generate profits, structure contracts, and justify their role in the drug channel.
For 2025, DCI estimates that total prescription dispensing revenues at retail, mail, long-term care, and specialty pharmacies reached $751 billion in 2025, up 10% from the 2024 figure.
GLP-1 agonist drugs have become the dominant driver of revenue growth. Over the past five years, increases in dispensing revenues from GLP-1 products accounted for about 60% of retail pharmacies’ total revenue growth.
The table below—one of 270 in our new report—racks up DCI's first look at the 15 largest organizations that competed for a share of those dollars. For a sneak peek at the complete report, click here to download our free 32-page report overview (including key industry trends, What's New in this edition, the Table of Contents, and a List of Exhibits).
Today’s guest post comes from Stephen Hom, Co-Founder, EVP & Chief Operating Officer of RIS Rx.
Drawing on RIS Rx’s proprietary data and case studies, Stephen highlights patterns that can undermine patient support program effectiveness. He argues that a more data-driven approach can help manufacturers identify hidden risks, improve program performance, and ensure that affordability resources reach the patients they are intended to support.
It’s time for Drug Channels Institute’s latest exclusive analysis of the 340B contract pharmacy market, which continues to boom along with the overall program’s expansion.
However, our 2026 analysis finds that the contract pharmacy market is now entering a more mature phase characterized by consolidation, slower growth, and increasing dominance by the industry’s largest participants.
Below, we characterize the state of the marketplace:
Nearly two-thirds of the entire U.S. pharmacy industry participates as contract pharmacies for the 340B hospitals and federal grantees.
The number of 340B pharmacy locations declined for the third year, due largely to the retail pharmacy shakeout and manufacturers’ 340B policies.
Meanwhile, the total number of unique contract pharmacy/covered entity relationships continues to expand. Five multi-billion-dollar, for-profit, publicly traded pharmacy chains and pharmacy benefit managers (PBMs)—Cigna, CVS Health, UnitedHealth Group, Walgreens, and Walmart—now account for a record 77% of all relationships.
Read on for our latest analysis of this ever-expanding profit pool for pharmacies and PBMs. For a deep dive on what the 340B program’s growth means for drug channel participants, join Adam J. Fein, Ph.D., and Tyler Novotny on June 12 for a new live video webinar: 340B in 2026: Market Shifts, Policy Battles, and What They Mean for Stakeholders.






 By

 By

 By


